High-quality CPR requires more than simply performing chest compressions. The rate and depth of compressions, chest recoil, interruptions, and ventilation all affect how effectively CPR supports circulation during cardiac arrest.
Understanding these components helps rescuers recognize what effective CPR should look like and maintain proper technique throughout resuscitation.
This guide covers the five components of high-quality CPR, recommended performance targets, ways to maintain CPR quality, and common mistakes to avoid.
What Is High-Quality CPR?
High-quality CPR refers to resuscitation performed according to recommended standards for effective chest compressions, complete chest recoil, limited interruptions, and appropriate ventilation. These elements help maintain blood flow to the brain and other vital organs during cardiac arrest.
Maintaining consistent performance throughout the process helps provide continuous support until a pulse returns or advanced treatment takes over.
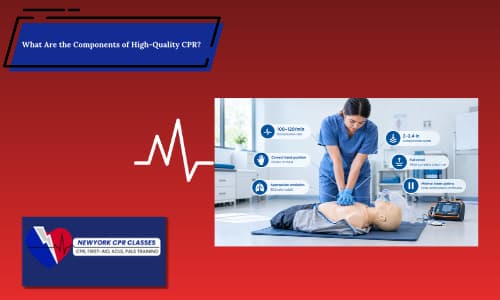
Five Components of High-Quality CPR
The five components of high-quality CPR are:
- Compression rate
- Appropriate compression depth
- Complete chest recoil after each compression
- Minimizing interruptions in chest compressions
- Avoiding excessive ventilation
Each component affects how effectively CPR maintains circulation during cardiac arrest. Even small changes in compression performance or unnecessary pauses can affect the quality of resuscitation.
1. Maintain the Correct Compression Rate
Chest compressions should be performed at 100 to 120 compressions per minute for adults, children, and infants. Maintaining this rate helps keep compressions consistent while allowing adequate depth and complete chest recoil.
The goal is not simply to reach a certain number of compressions. Rescuers should maintain the recommended rate while also ensuring that each compression reaches the appropriate depth and the chest fully recoils before the next compression.
2. Use the Appropriate Compression Depth
Compression depth varies by age. For adults, each chest compression should push the chest down at least 2 inches (5 cm). Avoid compressing deeper than 2.4 inches (6 cm).
For children and infants, compress the chest at least one-third of its anterior-posterior diameter. This is approximately 2 inches (5 cm) for children and 1.5 inches (4 cm) for infants.
Adequate depth helps generate effective blood flow during cardiac arrest. Compressing too shallowly may reduce the effectiveness of CPR, while excessive depth in adults can increase the risk of injury.
3. Allow Complete Chest Recoil
The chest should return fully to its normal position after each compression. Rescuers should release pressure after each compression and let the chest return fully to its normal position before the next compression
Complete recoil is important across adult and pediatric CPR. Maintaining pressure on the chest can interfere with the filling of the heart between compressions and reduce the effectiveness of CPR.
4. Minimize Interruptions in Chest Compressions
Chest compressions should be interrupted as little as possible. Necessary pauses may occur for ventilation, rhythm analysis, defibrillation, or other interventions, but they should be kept as short as possible. For infants and children, the 2025 AHA pediatric guideline specifically recommends keeping pauses in chest compressions below 10 seconds.
Chest compression fraction (CCF) measures the proportion of the resuscitation period during which chest compressions are being performed. For adults, the 2025 AHA guideline identifies 60% as a minimum target, while high-performance teams may achieve levels above 80%. Current pediatric guidance does not establish a specific CCF threshold for infants and children.
Keeping necessary transitions efficient, switching compressors when needed, and resuming compressions promptly after defibrillation can help reduce unnecessary pauses.
5. Avoid Excessive Ventilation
Ventilation should provide effective breaths without delivering too many breaths or excessive volume. During adult CPR without an advanced airway, rescuers generally provide 30 compressions followed by 2 breaths, with each breath delivered over about 1 second and enough volume to produce visible chest rise.
For infants and children without an advanced airway, the recommended compression-to-ventilation ratio is 30:2 for a single rescuer and 15:2 for two rescuers.
How to Maintain High-Quality CPR
Maintaining effective CPR requires more than getting the initial compression technique right. Rescuers also need to manage fatigue, monitor compression performance, limit pauses, and coordinate interventions without unnecessarily interrupting chest compressions.
Change the Compressor When Needed
Chest compression depth can begin to decline after about 90 to 120 seconds of CPR as fatigue develops. When multiple rescuers are available, changing the person performing compressions about every 2 minutes can help maintain compression quality. The transition should be coordinated to keep the interruption in compressions as short as possible.
Use CPR Feedback When Available
Audiovisual feedback devices can provide real-time information about compression rate, depth, and other aspects of CPR performance. For adults, the 2025 AHA guidelines state that these devices can reasonably be used to optimize CPR performance. Similar feedback may also be used during pediatric CPR as part of a broader quality improvement system.
Use an AED as Soon as It Is Available
An AED should be used as soon as it becomes available during cardiac arrest. Continue CPR while the device is being prepared, then follow its instructions for rhythm analysis and shock delivery. After the shock is delivered, resume chest compressions immediately. Avoid any unnecessary pause before restarting CPR.
Keep Necessary Pauses Short
Some interruptions are necessary during CPR, including rhythm analysis, defibrillation, and compressor changes. Keep these pauses as brief as possible and resume compressions promptly after the intervention. Reducing unnecessary interruptions helps maintain chest compression fraction and overall CPR quality.
Performing high-quality CPR during an emergency in New York can be difficult without regular hands-on practice. Enrolling in an AHA BLS class can help you develop and practice the skills needed to respond effectively and perform CPR with proper technique and confidence.
How Is CPR Quality Monitored?
CPR performance can be monitored throughout a resuscitation to identify changes in technique and maintain consistent performance. Teams may track measures such as chest compression fraction, compression quality, pauses, ventilation, and changes in performance over time.
Audiovisual feedback devices can provide real-time information during CPR, allowing rescuers to see whether their compressions are meeting recommended targets. This can help the team recognize declining performance, correct technique, and maintain consistent CPR quality.
Common Mistakes to Avoid During CPR
Several common problems can interfere with effective CPR:
- Compressing too slowly: A rate below the recommended 100 to 120 compressions per minute can reduce effective blood flow during CPR.
- Compressing too shallowly: Compressions that do not reach the recommended depth may not provide enough blood flow to vital organs.
- Compressing deeper than recommended: Excessive compression depth can increase the risk of injury without improving CPR effectiveness.
- Leaning on the chest between compressions: Remaining pressure on the chest prevents full recoil and can reduce blood flow during CPR.
- Taking unnecessary pauses: Longer interruptions reduce the time spent performing chest compressions and lower chest compression fraction.
- Delaying compressions after defibrillation: CPR should resume promptly after a shock to minimize the interruption in chest compressions.
- Providing excessive ventilation: Giving breaths too frequently or with excessive volume can interfere with effective CPR and may reduce blood flow.
- Allowing fatigue to reduce compression quality: Rescuer fatigue can cause compression depth and technique to decline, making timely compressor changes important.
Recognizing these common mistakes helps rescuers correct their technique and maintain effective CPR throughout resuscitation.
Prepare for Effective CPR Response
High-quality CPR depends on consistent compression performance, complete chest recoil, minimal interruptions, and appropriate ventilation. Understanding these key elements helps rescuers recognize effective CPR and maintain proper technique throughout resuscitation.
New York CPR Classes offers AHA BLS, ACLS, and PALS courses at multiple training locations throughout New York. This allows you to complete your training without traveling far from your location. After you successfully complete the course, you receive your AHA Provider eCard on the same day. The credential is nationally recognized and valid throughout the United States.
FAQs About High-Quality CPR
Does high-quality CPR improve the chances of survival?
Yes. High-quality CPR helps maintain blood flow during cardiac arrest, which supports the heart and brain until circulation is restored or advanced treatment is provided. The AHA identifies high-quality CPR as a critical intervention during cardiac arrest.
What is the difference between high-quality CPR and regular CPR?
High-quality CPR follows specific performance targets for compression rate, depth, recoil, interruptions, and ventilation. Regular CPR may involve the same basic actions but does not necessarily meet all recommended quality measures.
Is hands-only CPR considered high-quality CPR?
Hands-only CPR can be an appropriate form of CPR for an untrained bystander responding to a sudden adult cardiac arrest. It involves calling emergency services and providing continuous chest compressions in the center of the chest.
When should CPR be stopped?
CPR should be stopped when the person shows signs of life, a trained responder takes over, the scene becomes unsafe, or the rescuer is physically unable to continue.
While performing high-quality CPR, what action should be accomplished?
Maintain chest compressions at the recommended rate and depth, allow complete chest recoil, minimize interruptions, and provide appropriate ventilation. These actions help maintain effective blood flow throughout CPR.
What are the 3 components of high-quality CPR?
The five-component framework is widely used to describe high-quality CPR. When a question asks for three components, it usually refers to compression rate, compression depth, and minimizing interruptions.
Does high-quality CPR require rescue breaths?
Not always. Hands-only CPR is recommended for certain adult out-of-hospital cardiac arrests when a bystander is unwilling or unable to provide breaths. Conventional CPR with rescue breaths remains important in situations where ventilation is needed, including pediatric emergencies and some causes of cardiac arrest.
How quickly should CPR begin after cardiac arrest is recognized?
Chest compressions should begin as soon as cardiac arrest is recognized. Delaying CPR reduces the time during which blood flow is being supported, so assessment and activation of emergency response should occur without unnecessary delay.
Why is early AED use important during CPR?
An AED can identify certain shockable heart rhythms and deliver a defibrillation shock when indicated. High-quality CPR should continue while the AED is being prepared, with interruptions kept as short as possible around rhythm analysis and shock delivery.
Can high-quality CPR be performed by an untrained bystander?
Yes. Bystanders can provide CPR even without formal healthcare training. For a suddenly collapsed adult, the AHA recommends hands-only CPR for people who witness the event and are not trained or are unable to provide rescue breaths.
During high-quality CPR, when do rescuers switch roles?
During high-quality CPR, rescuers should generally switch the person performing chest compressions about every 2 minutes or sooner if the compressor becomes fatigued. The change should be coordinated to keep the interruption in compressions as short as possible.